1
Testicular Hyperthermia
Persistent venous pooling increases scrotal temperature and may interfere with normal spermatogenesis and testicular cell function.








Diagnosed with low sperm count (oligozoospermia), poor motility, or zero sperm (azoospermia)? This page explains how varicocele can affect testicular function, sperm DNA fragmentation and fertility, and how microsurgical repair fits into fertility planning.

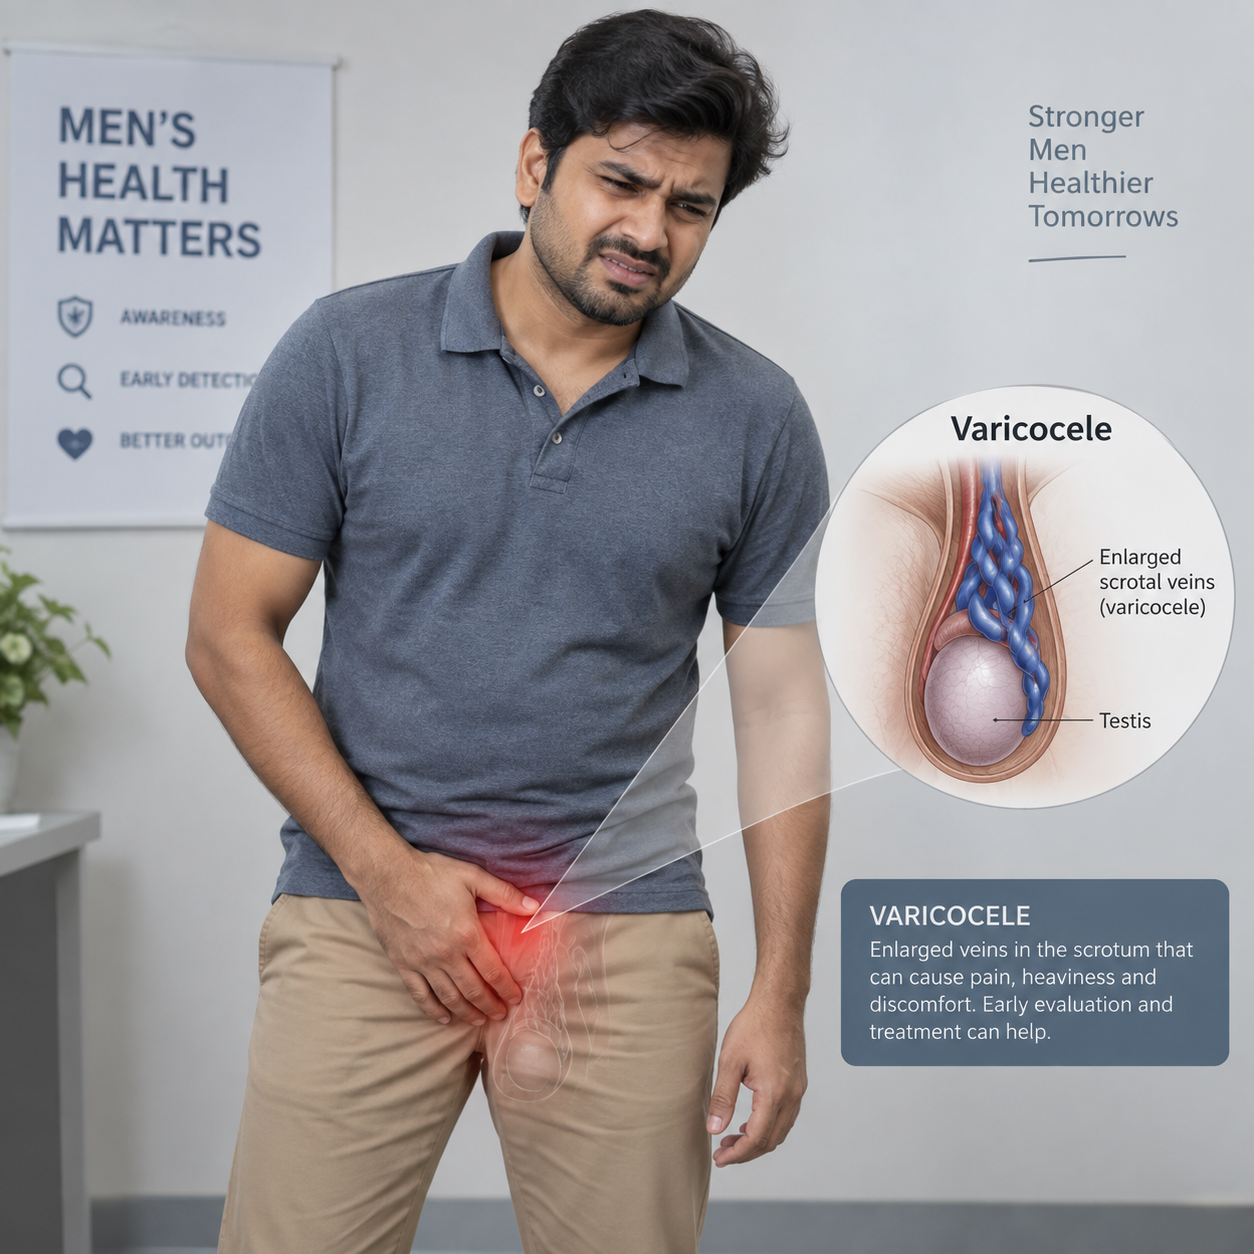
Varicocele is described in the supplied material as a common correctable cause of male infertility. Faulty venous valves in the pampiniform plexus allow blood to pool around the testicle, which can disturb the environment required for normal sperm production.
Persistent venous pooling increases scrotal temperature and may interfere with normal spermatogenesis and testicular cell function.
The supplied content links venous stasis with oxidative stress and a higher sperm DNA Fragmentation Index (DFI).
Chronic venous backpressure is described as potentially affecting Leydig cell function and testosterone production.
Many infertile couples are advised to proceed directly to IVF or ICSI even when a palpable varicocele is present. The supplied content argues that addressing the male factor first may improve sperm quality and change the fertility pathway for selected couples.

A side-by-side presentation of the treatment comparison supplied for this page.
| Clinical Parameter | Subinguinal Microsurgery (COMET) | Varicocele Embolization (IR) | Direct IVF / ICSI (Without Repair) |
|---|---|---|---|
| Primary Target | Definitive biological cure; preserves testicular artery & lymphatics | Venous occlusion via foreign metal coils & chemical sclerosants | Bypasses root male cause; relies entirely on female intervention |
| Recurrence Rate | <1% (near 0% with microsurgical magnification) | 10% to 20% (missed microscopic collaterals) | Not applicable |
| Bilateral Technical Failure | Near 0% (direct anatomical visualisation) | Up to 19.3% (right gonadal vein cannulation failure) | Not applicable |
| Radiation Hazard | Zero radiation | Direct X-ray fluoroscopy exposure to gonads | Zero radiation |
| Fertility Improvement | Significantly lowers DNA fragmentation; enhances natural pregnancy | Variable fertility outcomes; foreign glue/coil inflammation risks | Elevated miscarriage rate if sperm DNA damage remains high |
Watch the supplied doctor-led videos on low sperm count, fertility outcomes and microsurgical treatment.



The supplied content explains that spermatogenesis works on a roughly 72–90 day cycle, so semen improvement is assessed over months rather than days.
Testicular venous congestion clears, hyperthermia stops and active inflammation resolves.
The source describes this period as the first useful follow-up window for sperm motility and morphology changes.
The supplied content describes this period as a key window for improvement in total motile sperm count and natural conception planning.
10 practical answers to recurring patient questions about low sperm count, motility, azoospermia, natural pregnancy, IVF / ICSI and fertility recovery after varicocele treatment.
Yes. Varicocele can cause low sperm count or poor sperm motility in some men by increasing testicular temperature and oxidative stress. This may affect sperm concentration, progressive motility and morphology. Not every man with a varicocele has an abnormal semen report, so fertility planning should combine examination, Doppler findings and a properly performed semen analysis.
Starts 00:00
Sperm count can increase after varicocele microsurgery in selected men, but no operation can guarantee a specific number. Improvement in sperm count, motility or morphology depends on the starting semen parameters, testicular function, duration of infertility, varicocele severity and other male- and female-factor fertility issues.
Starts 03:20
Sperm count or motility improvement after varicocele surgery is usually assessed over months, not days. Because sperm production takes roughly 72 to 90 days, the first semen review is commonly around 3 months. Changes may become clearer between 3 and 6 months and can continue to evolve over 6 to 12 months.
Starts 06:30
Natural pregnancy after varicocele surgery is possible, particularly when semen parameters improve and there is no major female-factor fertility problem. It is not guaranteed. The chance of natural conception depends on both partners, including female age, ovarian reserve, duration of infertility and the man’s post-treatment semen quality.
Starts 08:10
Varicocele surgery before IVF or ICSI may be discussed for selected infertile men who have a palpable clinical varicocele and abnormal semen parameters. The decision also depends on the female partner’s age and ovarian reserve, how long the couple has been trying, previous IVF or ICSI history, and whether assisted reproduction should not be delayed.
Starts 02:00
Grade 1 or Grade 2 varicocele can be associated with infertility or abnormal semen parameters, but the grade alone does not prove that the varicocele is the cause. Clinical grade should be considered together with semen analysis, testicular size, symptoms, Doppler reflux and the couple’s fertility history before treatment is planned.
 Starts 01:20
Azoospermia or zero sperm may improve after varicocele treatment in selected men with non-obstructive azoospermia and a clinical varicocele, but this is not predictable or guaranteed. Zero sperm has many possible causes, so hormonal testing, examination and a complete male-infertility evaluation are essential before attributing azoospermia to varicocele.
 Starts 03:30
Yes. If sperm count is normal but motility is low, varicocele can still be relevant because it may affect progressive motility, morphology and sperm DNA quality as well as concentration. Repeat semen testing and the complete fertility picture are more useful than judging treatment from sperm count alone.
Starts 03:20
Bilateral varicocele can affect fertility, but both sides do not automatically need treatment. Each side should be examined separately and correlated with Doppler reflux, testicular size and semen findings. Bilateral microsurgery is planned when both sides are clinically significant and repair is justified.
 Starts 03:20
Medicines or supplements may support semen health in selected men, especially when a nutritional deficiency or another reversible factor is present, but medicines and antioxidants do not correct the abnormal venous reflux of a clinical varicocele. When low sperm count is associated with a palpable varicocele and abnormal semen parameters, the role of repair should be discussed rather than relying only on supplements.
 Starts 03:30
Share your Doppler ultrasound, semen analysis, sperm DNA fragmentation report if available, and previous fertility treatment records for a focused varicocele and male-fertility consultation.
+91-95929 99184